Author: Sabina Paglialunga

  • How Healthy Volunteer Studies can Accelerate Oncology Drug Development

    By Sabina Paglialunga, PhD & Aernout van Haarst, PhD; Senior Directors Scientific Affairs, Celerion

    Traditional drugs to treat cancer include chemotherapies, which are cytotoxic agents that non-specifically interrupt cell growth. While chemotherapy drugs effectively obstruct tumor development and growth, they also affect healthy cells, which can result in serious side effects as well as additional malignancies. Over the past two decades, alternative targeted therapies have emerged as less toxic options. Specifically, these drugs are designed to target and inhibit distinct molecular pathways involved in cancer cell growth and survival, such as tyrosine, serine, or threonine kinases. These enzymes and their receptors tend to be overexpressed in tumor cells and are involved in tumor cell proliferation, migration, and angiogenesis.

    Compared to conventional chemotherapies, kinase inhibitors are generally considered non-cytotoxic compounds and, therefore, can be administered to healthy volunteers, especially for early-phase clinical pharmacology studies. This approach not only de-risks clinical investigations in patients but can also accelerate drug development. Robust safety and pharmacokinetic (PK) data can be acquired from healthy volunteers for first-in-human (FIH), food effect, and drug-drug interaction (DDI) studies with efficiency, quality, and swiftness.

    Advantages of Healthy Volunteers over Patients:

    • More resilient human population if adverse events (AEs) occur:
      • AEs tend to be transient in nature, and healthy volunteers recover faster than patients do
    • Potential for less variable data
      • Healthy volunteers are not confounded by comorbidities that could result in data variability
    • Healthy volunteers are easier to recruit than most patient populations:
      • During early phase development, when efficacy has yet to be established, there is no potential benefit for patients, which may impact motivation to participate in a clinical trial
    • Patients are a more fragile population:
      • Due to polypharmacy, there may be potential drug interactions
    • Effect of disease on AE profiles:
      • In patient studies, care must be taken to distinguish drug-related AEs vs natural disease progression
    • Time and cost savings:
      • Development costs can be substantial as patient studies tend to require multiple sites, and slower recruitment can impact timelines

    In general, unless the investigational compound causes direct DNA damage, regulatory agencies typically allow the administration of healthy volunteers. Overall, tyrosine kinase inhibitors tend to have an acceptable safety profile that justifies administration in healthy subjects. Nonetheless, they are known to elicit certain adverse effects, such as skin reactions, hepatotoxicity, and cardiovascular and gastrointestinal side effects, yet several mitigation steps can be taken to prevent or overcome these common class AEs.

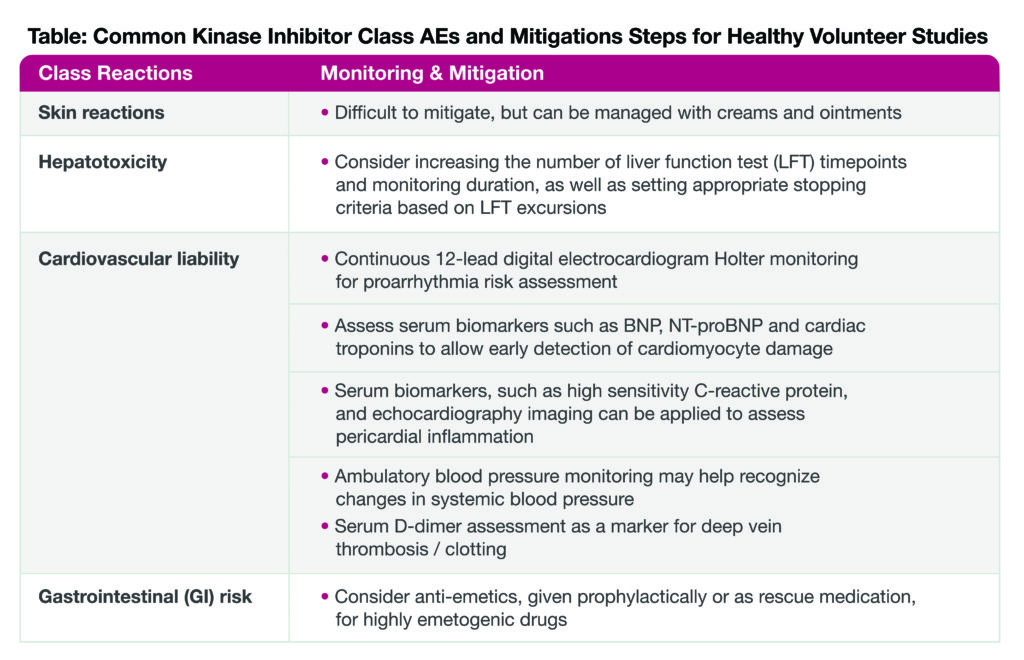
    CEL CommonKinaseInhibitor graphic 091024B

    Product Labeling Studies to Support Regulatory Submission

    GI effects are quite common with kinase inhibitors; many cancer patients take acid-reducing agents (ARA) to help manage these side effects. The prevalence of ARA usage ranges between 20-70%, depending upon the cancer type, with GI and pancreatic cancers being the most widespread for ARA treatment. This is relevant for drug developers because of potential drug interactions between the kinase inhibitor and ARAs. In general, ARAs raise the stomach pH, making it a less acidic environment; this could reduce or increase drug bioavailability, which in turn could decrease efficacy or compromise safety, respectively.

    Recent FDA guidance provides a physiochemical framework when an ARA-drug interaction study is recommended. Proton-pump inhibitors (PPIs) are the class of ARAs typically evaluated in such DDI studies as they are considered a worst-case scenario due to their relatively strong and long-standing effects on stomach pH. Typically, these PPI studies enroll healthy volunteers and can be combined with a non-medicinal ARA (e.g. orange juice, coke) or food effect arm in a single study design to maximize data output and understand how ‘real word’ factors will impact drug PK.

    In addition to ARA DDI trials, other “drug labeling studies” that can be conducted in healthy volunteers include ADME, bioavailability(BA) / bioequivalent (BE), food effect, DDIs, and cardiac safety (TQT) assessments. These studies can support drug label claims and regulatory submissions. Conducting these studies in healthy volunteers allows for robust, high-quality data to be captured quickly.

    Conclusions

    In general, healthy, normal subjects can be considered for non-cytotoxic, small-molecule clinical trials, such as FIH, ADME, food effect, DDI, and cardiac safety (TQT) studies. Overall, Celerion has conducted over 140 clinical trials with kinase inhibitors since 2010. Relying on our extensive experience, we know how specific risks can best be mitigated. By leveraging data quality and saving time and costs, healthy volunteer oncology studies play a crucial role in accelerating cancer drug development, ensuring that only the most promising candidates proceed to patient populations at the safest dosing regimen.

    Learn more about our Product Labeling Clinical Pharmacology Studies on our resource page, or contact us at: info@celerion.com.
  • Celerion’s US Pharmacies Expand On-Site Services, Ensure cGMP FDA Compliance for Phase 1 Investigational Drugs

    LINCOLN, Neb.; July 17, 2024 (Business Wire) – Celerion, a leading clinical research organization specializing in early clinical research and bioanalytical services, announces the launch of on-site services for rapid sterility testing (validated alternative method to USP <71>) and dose formulation analysis.

    Per FDA guidance, pharmaceutical products intended for parenteral administration must undergo sterility testing and provide results that meet stringent safety standards before reaching patients. Additionally, laboratory testing of Phase 1 investigational drugs must be completed to evaluate quality attributes including identity, strength, potency, and purity. Celerion’s comprehensive approach includes a fully integrated pharmacy and analytical laboratory facility.

    Celerion’s on-site pharmacy allows for “just in time” flexible formulation, saving clients time and money. Leveraging state-of-the-art equipment and expert analysis, Celerion refines pharmaceutical dosage formulations efficiently and effectively. This enables seamless compound analysis and testing, optimizing efficiency, speed, and control throughout development and testing phases.

    “Offering comprehensive analysis and testing capabilities under one roof provides sponsors with rapid, reliable solutions that meet regulatory requirements without compromising quality,” said Chad Briscoe, Ph.D., Executive Vice President, Global Bioanalytical Sciences.

    “In the face of evolving regulations, timely access to accurate sterility test results is paramount,” said Phil Bach, Executive Vice President, Global Clinical Research. “Our in-house capabilities for sterility testing and analysis allow us to accelerate this critical step within our controlled environment, providing sponsors with unparalleled speed and development schedule oversight.”

    About Celerion
    Celerion, a global leader in early clinical research services, offers a unique combination of medical expertise, clinical operations experience, and scientific excellence that gives its clients the confidence to make fast, accurate decisions about their drug development path.

    For over fifty years, Celerion has leveraged the latest operational concepts and technologies to execute safety/tolerability, pharmacokinetic, and pharmacodynamic studies in highly controlled clinical environments. These include first-in-human dose escalation, drug-drug interaction, cardiac safety, bioequivalence and bioavailability, metabolism, and excretion studies, as well as pharmacokinetic evaluations in patients with impaired renal or hepatic function. In addition, Celerion offers data management, biostatistics, clinical monitoring, and bioanalytical services. Our founding mission is to help our clients get their drugs to market quickly, so that they touch the lives of our family, friends, and people in need around the world. For more information, please visit www.celerion.com.

  • Celerion Honored With Prestigious CRO Leadership Award for Ninth Consecutive Year 

    LINCOLN, Neb.; June 5, 2024 (Business Wire) – Celerion, a leading clinical research organization, is pleased to announce it has received a CRO Leadership Award for the ninth time by global biopharmaceutical executives in Life Science Leader’s annual CRO Leadership Awards for 2024. 

    Celerion was distinguished among 42 of their peers in the annual Contract Research Quality Benchmarking online survey conducted by Industry Standard Research. Celerion was recognized as a CRO Leader in the quality, capabilities and reliability categories across two groups of respondents (small pharma and combined big and small pharma). 

    “We are deeply honored to receive this award, which reaffirms our commitment to helping our clients bring life-changing medicines to market,” said Celerion CEO Susan Thornton, Ph.D. “This achievement would not have been possible without the trust and collaboration of our valued clients. We extend our heartfelt gratitude to them for their partnership in driving meaningful progress and improving patient outcomes.” 

    About Celerion 

    Celerion, a global leader in early clinical research services, offers a unique combination of medical expertise, clinical operations experience, and scientific excellence that gives its clients the confidence to make fast, accurate decisions about their drug development path. 

    For over fifty years, Celerion has leveraged the latest operational concepts and technologies to execute safety/tolerability, pharmacokinetic, and pharmacodynamic studies in highly controlled clinical environments. These include first-in-human dose escalation, drug-drug interaction, cardiac safety, bioequivalence and bioavailability, metabolism, and excretion studies, as well as pharmacokinetic evaluations in patients with impaired renal or hepatic function. In addition, Celerion offers data management, biostatistics, clinical monitoring, and bioanalytical services. Our founding mission is to help our clients get their drugs to market quickly, so that they touch the lives of our family, friends, and people in need around the world.

  • Key Clinical Pharmacology Studies to Support Biologic Drug Regulatory Submission

    By Sabina Paglialunga, PhD  & Aernout van Haarst, PhD; Senior Directors Scientific Affairs, Celerion

    Biologic drugs are pharmaceutical products derived from living organisms or their components. They represent a wide range of therapeutic treatments that include monoclonal antibodies, proteins, peptides as well as cell and gene therapies.  Oligonucleotide therapeutics, on the other hand, may in principle be synthetic drugs, but by targeting specific RNA sequences to alter RNA and/or protein expression, they share certain features of true biologics. Generally, biologics and oligonucleotide drugs offer several advantages over traditional small molecule products such as targeted therapy,  longer half-life (which can be associated with less frequent dosing leading to greater patient adherence) and even higher potency resulting in greater effectiveness. However, unlike most small molecules, plasma pharmacokinetic (PK) profiles of biologics and oligonucleotides may not reflect the target tissue distribution therefore, in some cases appropriate biomarkers or measures of target engagement may need to be assessed as an equivocal dose-effect relationship.

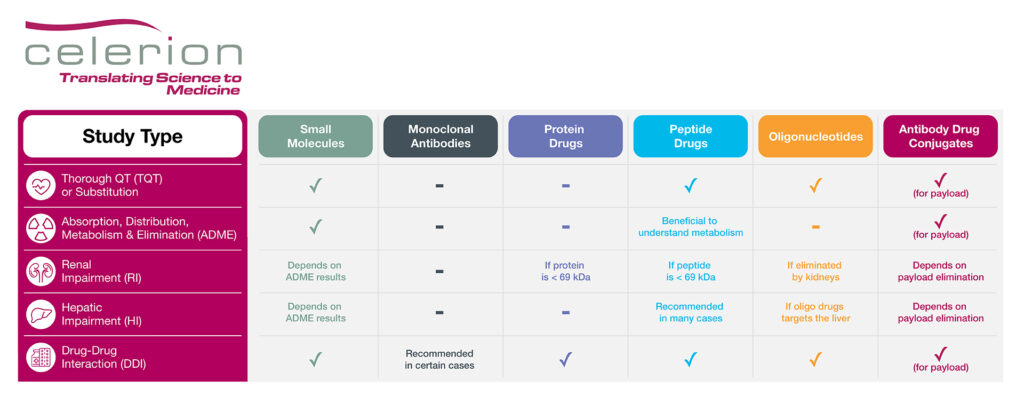
    With biologics and oligonucleotide drugs playing an important role in modern medicine, over the past few years the FDA has issued updated guidance for oligonucleotides (draft 2022), peptides (draft 2023) and antibody drug conjugates (ADC; final 2024) to further promote these areas of drug development. Notably, many of the clinical pharmacology studies recommended to support small molecule regulatory submission, as well as efficiencies in corresponding study designs, may also pertain to biologics and oligonucleotide drugs. For example, if safe to do so, enrollment of healthy volunteers (HV) can expedite drug development, as this group is faster to recruit, associated with less variability in PK data, and have no confounding co-morbidities or concomitant medications compared to patients. The below table highlights which key clinical pharmacology studies may be recommended for each drug type.

    Table: Key Clinical Pharmacology Studies to Support Drug Regulatory Submission

    Product Labeling Clinical Pharmacology Studies

    While large biologic drugs such as monoclonal antibodies and proteins are exempt from cardiac proarrhythmia risk assessment, a dedicated thorough QT (TQT) study may be recommended for peptide and oligonucleotide drugs, especially if a TQT substitution request via IHC E14 Q&A 5.1 or 6.1 is not sought.

    A mass balance study employing a radiolabel is typically recommended for small molecules to understand and track adsorption, distribution, metabolism and elimination (ADME) of the parent drug. While not necessary for biologic and oligonucleotide drugs, there may be cases where an ADME study could be beneficial for peptide products, especially if their distribution and elimination pathways are unknown.  The ADME study could also help inform the necessity of organ insufficiency PK studies, such as renal or hepatic impairment studies.  For instance, if a protein or peptide drug is < 69 kDa, meaning small enough to be filtered by the kidneys, a renal impairment study is recommended.  Similarly, a renal impairment PK study is recommended for oligonucleotide drugs if the therapeutic product is substantially eliminated by the kidneys. In addition, if the oligonucleotide drug targets the liver as part of its mechanism of action, a hepatic impairment PK study should be conducted. Peptides tend to be rapidly degraded by proteases and peptidases, bypassing hepatic elimination, thus negating the need for a hepatic impairment study. However, the recent draft FDA guidance document on peptide drug development does recommend a hepatic impairment PK study under certain conditions, such as:

    • The peptide drug is anticipated to undergo substantial hepatic metabolism or biliary excretion
    • The (lipid-conjugated) peptide drug is highly bound to serum albumin
    • The peptide drug’s pharmacological activity affects normal liver function

    Finally, a drug-drug interaction (DDI) study may be recommended if the biologic or oligonucleotide product is a CYP or transporter substrate or modulator, or if a PD interaction with a concomitant medication is anticipated. For example, glucagon like protein-1 (GLP-1) analogs may delay gastric emptying, thereby affecting the absorption of co-administered treatments. In addition, therapeutic proteins that are proinflammatory cytokines or up/down-regulate cytokines levels may also need to be evaluated for DDI potential. 

    Special Considerations for ADC Drug Development

    ADCs combine both small molecule and biologic drug components. The small molecule, often referred to as a ‘payload’, is conjugated to an antibody or an antibody fragment via a chemical linker. The antibody portion of the drug directs the payload to a specific tissue or target cell. Due to the combination of small molecule and biologic drug aspects, clinical pharmacology studies may be recommended to assess the unconjugated payload as well as the ADC or the total antibody, as necessary. 

    Conclusion

    Clinical pharmacology studies such as TQT/cardiac safety, ADME, renal & hepatic impairment or DDI trials may be recommended for biologic and oligonucleotide drug development, depending on the type, size, PK profile and/or PD effects of the product. Celerion’s experienced team of scientific and operational experts are ready to support your biologic drug development program with efficient protocol design, effective study conduct and reliable data management & analysis. 

    Learn more about our Product Labeling Clinical Pharmacology Studies on our resource page, or contact us at:  info@celerion.com.

  • Jo Goodman Joins Celerion as Vice President of Bioanalytical Services

    LINCOLN, Neb.; May 7, 2024 (Business Wire) – Celerion, a leading clinical research organization, specializing in early clinical research and bioanalytical services, today announced the appointment of Jo Goodman as Vice President of Bioanalytical Services in its Lincoln, Nebraska, laboratory.

    In her new role, Goodman will oversee the strategic direction and operational performance of the Lincoln bioanalytical laboratory, leveraging her extensive experience in pharmaceutical research and development to drive innovation and design and execute customized bioanalysis for clients’ needs. She will be responsible for delivering on Celerion’s bioanalytical promise of industry-leading science, stringent compliance, and speed of delivery.

    With over 29 years of experience in the pharmaceutical industry, Goodman brings a wealth of knowledge in regulated GxP and discovery bioanalysis for both in-house and outsourced activities. Prior to joining Celerion, she held positions of increasing responsibility at AstraZeneca, MedImmune, and GlaxoSmithKline. Additionally, Goodman is a recognized thought leader, having recently served as a member of the Expert Working Group (EWG) for ICH M10 Bioanalytical Guidance Development and is active in numerous non-profit industry consortia such as EBF, AAPS, and DMDG.

    “We are delighted to welcome Jo Goodman to our team,” says Dr. Chad Briscoe, Celerion’s executive vice president of global bioanalytical services. “Her proven track record of leadership, globally recognized reputation, and expertise in bioanalytical services will be invaluable as we continue to expand our capabilities and provide superior solutions to our clients.”

    About Celerion
    Celerion, a global leader in early clinical research services, offers a unique combination of medical expertise, clinical operations experience, and scientific excellence that gives its clients the confidence to make fast, accurate decisions about their drug development path.

    For over fifty years, Celerion has leveraged the latest operational concepts and technologies to execute safety/tolerability, pharmacokinetic, and pharmacodynamic studies in highly controlled clinical environments. These include first-in-human dose escalation, drug-drug interaction, cardiac safety, bioequivalence and bioavailability, metabolism, and excretion studies, as well as pharmacokinetic evaluations in patients with impaired renal or hepatic function. In addition, Celerion offers data management, biostatistics, clinical monitoring, and bioanalytical services. Our founding mission is to help our clients get their drugs to market quickly, so that they touch the lives of our family, friends, and people in need around the world. 

    Media Contact: 
    Michelle Maklas-Baker 
    Associate Director, Global Marketing 
    +1 732-306-7804 
    michelle.maklasbaker@celerion.com

  • 12 Questions to Help Guide Renal Impairment PK Study Design

    By Sabina Paglialunga, PhD  Director Scientific Affairs, Celerion

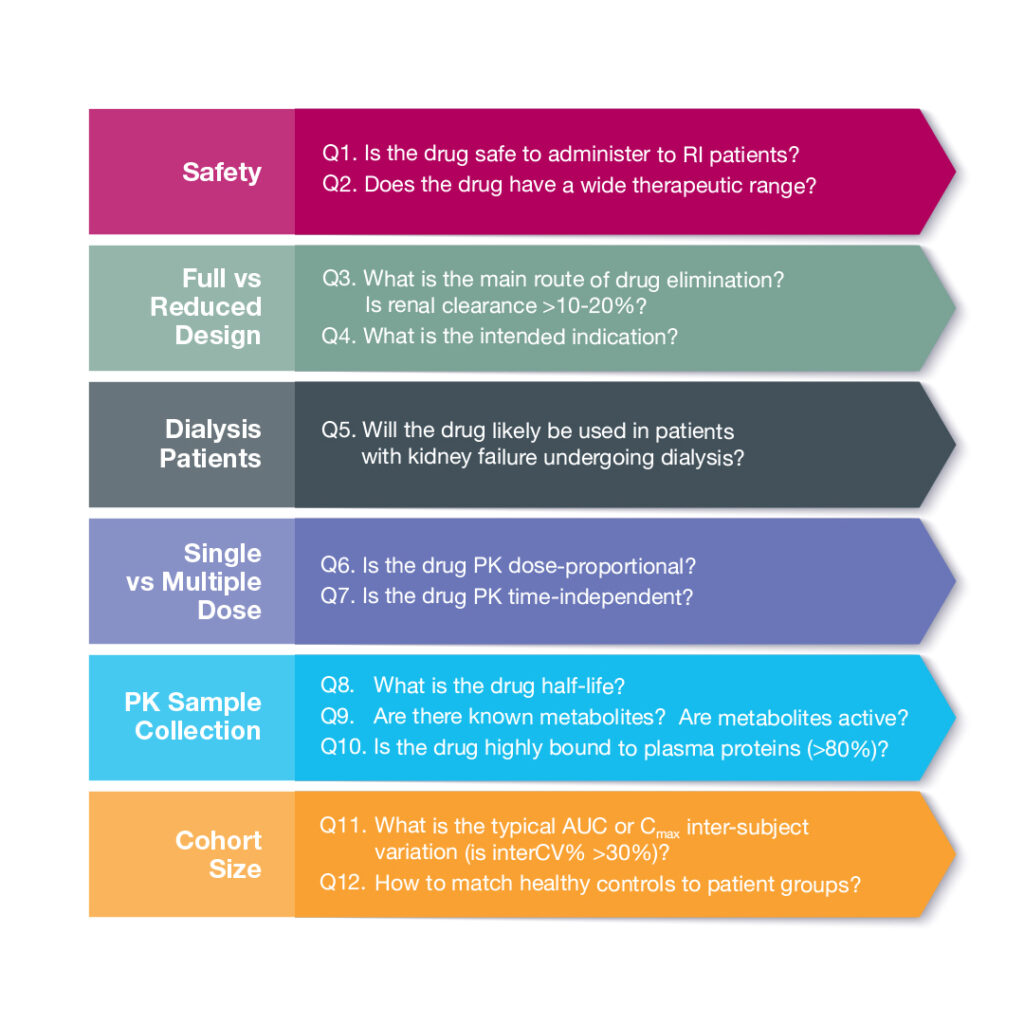
    Need to run a renal impairment pharmacokinetic (PK) study, but don’t know where to begin? We have  you covered! Celerion has managed more than 30 renal impairment PK studies over the past decade. We have a network of clinical sites and access to patients. To begin, we’ll guide you through 12 key questions to optimize study design.

    Safety First

    The first set of questions (Q1&2) relates to the safety profile of the drug in development. Is the investigational product safe to administer to patients with kidney dysfunction? If the study drug exacerbates kidney dysfunction, then it may not be suitable to dose in renal impaired participants. Next, we should consider the therapeutic range, as an increase in adverse events (AEs) and safety concerns may arise in patients with altered kidney function if the range is narrow.

    Design Foundations

    Assuming we are in the clear on these two fronts, we can then address the type of study needed (Q3&4). The FDA guidance, refers to full and reduced study designs. A full study explores the spectrum of organ dysfunction with cohorts ranging from normal → mild → moderate → severe, and in some cases kidney failure. A reduced study examines both ends of the continuum to compare normal vs severe conditions. If the investigational drug is mainly eliminated via the kidneys (i.e. renal clearance is > 10-20%) and/or is intended for patients with chronic kidney disease (CKD), then a full study is typically recommended. A reduced design is often sought when the investigational drug is likely to be administered to CKD patients yet the study drug is predominantly eliminated via the hepatobiliary route.

    A hemodialysis study (Q5) may be recommended if the study drug is likely to be used in patients undergoing dialysis; the drug is not highly bound to plasma protein, and is small enough to escape dialysis filtering.  In this case, the PK of the drug and any active metabolites are evaluated in patients both on- and off-dialysis days.  

    The dose regimen will depend on the PK characteristics of the study drug (Q6&7). A single dose may be administered if the drug exhibits dose-proportionality and displays time-independent PK. Multiple dose administration is often recommended when the drug or active metabolites show dose- or time-dependent PK characteristics.

    Sample Collection

    The following series of questions (Q8-10) help define the study sample schedule, collection, and analysis. In general, for renal impairment PK studies, blood samples are collected out to at least 3x the drug half-life. Metabolites representing >10% of total drug concentration should be measured in addition to the parent drug. If there is significant plasma protein binding, the unbound drug concentration should also be analyzed. Plasma protein binding is often altered in patients with renal impairment.  Per the FDA guidance, a limited number of unbound samples can be measured if binding is not concentration- or time-dependent. In this situation, we recommend to collect at least 2 time points per participant; one at baseline and one at Tmax.

    Cohort Size

    The next question to consider is the number of patients per cohort (Q11). The FDA guidance recommends a powered study and sample size justification based on PK variability. Depending on drug variability (interCV%), 9-14 patients per cohort may be recommended.

    Normal control matching is another question that regularly comes up during renal impairment study design discussions (Q12). We typically recommend the healthy control group to match patients by age (± 10 years), BMI (± 20%) and gender. There are two strategies, individual and mean matching. Individual or 1-to-1 matching allows for parallel patient and control enrollment, but can be difficult if a patient has uncommon characteristic. In some cases, a healthy control can match to more than one patient from different disease stage cohorts. With mean matching, the average values for the patient group are matched to the control subjects. This approach requires fewer subjects, but must wait until patient enrollment is complete. 

    Ready to Start

    With this information in hand, our team of operational and scientific experts can propose the ideal number of sites, recruitment timelines, and other study design considerations. Rely on Celerion for budget-friendly and streamlined processes that leverage our long-standing and established relationships with key renal impairment PK Principal Investigators.

    Check out our Renal/Hepatic Impairment PK Study Resource page for more information, or contact us at info@celerion.com

  • Celerion Achieves Milestone With CLIA Certification for Its Bioanalytical Laboratory, Expanding Capabilities in Clinical Trials and Diagnostic Testing

    LINCOLN, Neb.; Feb. 6, 2024 (Business Wire) – Celerion, a leading clinical research organization, proudly announces its recent achievement of obtaining the Clinical Laboratory Improvement Amendments (CLIA) certification for its state-of-the-art bioanalytical laboratory located in Lincoln, Nebraska. This significant milestone marks a pivotal step in Celerion’s commitment to advancing healthcare by integrating high complexity testing and diagnostic services into its comprehensive suite of bioanalytical solutions.

    Celerion’s clinical laboratories, including their Lincoln site, have been CLIA-certified and CAPaccredited for over 25 years, which helped facilitate the CLIA certification of the laboratory. The CLIA certification is a testament to Celerion’s adherence to the highest standards of laboratory quality and competence. It enables Celerion to conduct non-waived testing on human specimens, a critical component in the health assessment, diagnosis, prevention, and treatment of diseases. This certification is particularly crucial as it allows Celerion to perform these vital tests prior to the full accreditation inspection by a CMS-approved agency, ensuring continuous advancement in patient care and clinical research.

    With this certification, Celerion’s bioanalytical laboratory is now able to conduct lab-developed tests in specialized areas such as diagnostic immunology. These tests, recognized for their “high complexity” and stringent CLIA oversight, include but are not limited to ADA (anti-drug antibodies), NAb (neutralizing antibodies), and a wide array of biomarker assays. These assays are instrumental in determining patient inclusion and exclusion criteria for clinical trial enrollment, thereby enhancing the precision and efficacy of clinical studies. Moreover, the CLIA certification allows Celerion to engage in studies that require the reporting of patient-specific results. This capability is crucial for tailoring patient care and treatment, such as adjusting individual dosing based on specific data, distinct from the standard dosing for the general study population. This approach not only underscores the personalized aspect of patient care, but also significantly contributes to the optimization of therapeutic strategies and outcomes.

    Celerion’s Executive Vice President, Global Bioanalytical Sciences, Dr. Chad Briscoe, stated, “Achieving CLIA certification for bioanalytical assays is not just a milestone for Celerion, but a leap forward for the entire field of bioanalysis and clinical research. It underscores our unwavering commitment to quality, precision, and innovation. With this certification, we are poised to deliver enhanced value to our clients and contribute more profoundly to the advancement of healthcare and patient treatment options.”

    About Celerion

    Celerion, a global leader in early clinical research services, offers a unique combination of medical expertise, clinical operations experience, and scientific excellence that gives its clients the confidence to make fast, accurate decisions about their drug development path.

    For over fifty years, Celerion has leveraged the latest operational concepts and technologies to execute safety/tolerability, pharmacokinetic, and pharmacodynamic studies in highly controlled clinical environments. These include first-in-human dose escalation, drug-drug interaction, cardiac safety, bioequivalence and bioavailability, metabolism, and excretion studies, as well as pharmacokinetic evaluations in patients with impaired renal or hepatic function. In addition, Celerion offers data management, biostatistics, clinical monitoring, and bioanalytical services. Our founding mission is to help our clients get their drugs to market quickly, so that they touch the lives of our family, friends and people in need around the world. 

    Media Contact: 
    Michelle Maklas-Baker 
    Associate Director, Global Marketing 
    +1 732-306-7804 
    michelle.maklasbaker@celerion.com

  • Celerion Receives a 2023 CRO Leadership Award in All Categories for the Eighth Year Running

    LINCOLN, Neb.; May 10, 2023 (Business Wire) – Celerion, a leading clinical research organization, has been recognized for the eighth consecutive year as the winner of a CRO Leadership Award by global biopharmaceutical executives in Clinical Leader and Life Science Leader’s annual CRO Leadership Awards for 2023.

    Celerion was distinguished among 46 of their peers in the annual Contract Research Quality Benchmarking online survey conducted by Industry Standard Research. Celerion received a CRO Leadership Award in all five categories, including capabilities, compatibility, expertise, quality, and reliability.

    “We are honored to receive this prestigious recognition and would like to extend our sincere appreciation to our clients for their trust and support,” says Celerion CEO Susan Thornton, Ph.D. “This recognition is a reflection of our continued focus on innovation, quality, and customer satisfaction. We believe that our unwavering commitment to these principles is the foundation of our success and sets us apart from our competitors,” she added.

    About Celerion

    Celerion, a global leader in early clinical research services, offers a unique combination of medical expertise, clinical operations experience, and scientific excellence that gives its clients the confidence to make fast, accurate decisions about their drug development path.

    For over fifty years, Celerion has leveraged the latest operational concepts and technologies to execute safety/tolerability, pharmacokinetic, and pharmacodynamic studies in highly controlled clinical environments. These include first-in-human dose escalation, drug-drug interaction, cardiac safety, bioequivalence and bioavailability, metabolism, and excretion studies, as well as pharmacokinetic evaluations in patients with impaired renal or hepatic function. In addition, Celerion offers data management, biostatistics, clinical monitoring, and bioanalytical services. Our founding mission is to help our clients get their drugs to market quickly, so that they touch the lives of our family, friends and people in need around the world. 

    Media Contact: 
    Michelle Maklas-Baker 
    Associate Director, Global Marketing 
    +1 732-306-7804 
    michelle.maklasbaker@celerion.com

  • Celerion Expands Its Service Offering to Include GLP/GCP Compliant Molecular and Cell Biology Testing

    LINCOLN, Neb.; Nov. 10, 2022 (Business Wire) – Celerion, a clinical research organization (CRO) to the biopharmaceutical industry, announces the expansion of molecular and cellular capabilities to Good Laboratory Practice/Good Clinical Practice (GLP/GCP) standards to support the development of new modality therapies, such as cell and gene therapies. The expanded service offering is available in both of the company’s Lincoln and Zürich bioanalytical laboratories and includes ELISpot analysis, flow cytometry, and qPCR.                     

    Celerion’s expanded service offering provides platforms for immune monitoring and biomarker screening with high-throughput flow cytometry and ELISpot testing. Celerion has a pre-qualified interferon gamma ELISpot assay, allowing for a significantly faster validation process with study-specific antigens, thereby accelerating the development process for cell and gene therapies and vaccines alike. 

    Celerion also supports vaccine development programs by offering fully automated ELISA assays in a Biosafety Level 2 environment. 

    Flow cytometry is used to support the drug development of cell, gene, and immunotherapies with endpoints including immune-phenotyping of immune cells and receptor occupancy assessment. Celerion also provides high-throughput molecular biology testing for vector shedding analysis for gene therapies in compliance with current regulations as well as biodistribution to support GLP studies and transgene expression analysis using RT-PCR.

    “Our state-of-the-art cellular and molecular division has been built with the increased demand for new modalities in mind,” said Ray Farmen Ph.D., Vice President of Global Bioanalytical Sciences. “Celerion’s co-located clinical research facilities and bioanalytical laboratories enable timely method validation of many assays. We have qualified assays, validated analytical platforms, and trained staff available to quickly start your project and deliver to demanding timelines.”

    Farmen adds that Celerion has decades of regulatory experience, scientific excellence, and laboratory investments that enable accelerated development of these complex therapies. 

    About Celerion
    Celerion, a global leader in early clinical research services, offers a unique combination of medical expertise, clinical operations experience, and scientific excellence that gives its clients the confidence to make fast, accurate decisions about their drug development path.

    For over fifty years, Celerion has leveraged the latest operational concepts and technologies to execute safety/tolerability, pharmacokinetic, and pharmacodynamic studies in highly controlled clinical environments. These include first-in-human dose escalation, drug-drug interaction, cardiac safety, bioequivalence and bioavailability, metabolism and excretion studies, as well as pharmacokinetic evaluations in patients with impaired renal or hepatic function. In addition, Celerion offers data management, biostatistics, clinical monitoring, and bioanalytical services. Our founding mission is to help our clients get their drugs to market quickly, so that they touch the lives of our family, friends and people in need around the world. For more information, please visit www.celerion.com.

    Media Contact:

    Michelle Maklas-Baker
    Associate Director, Global Marketing
    1.732.306.7804
    michelle.maklasbaker@celerion.com

  • Adaptive Trial Designs

    Flexibility of Adaptive Early Phase Study Designs

    Sabina Paglialunga, PhD   Director, Scientific Affairs

    Adaptive clinical trials are characterized by innovative and flexible designs that incorporate safety and other information acquired during a study to instruct the next steps in a trial. Typically, these pre-planned adjustments include sample size refinement, subsequent dose level selection, or allocation ratio. In the case of patient studies, adaptive elements may consist of inclusion/exclusion criteria adjustment or stopping rules based on success or lack of efficacy [1].  Adaptive study designs are well established for cancer trials [2], and while they are applied to a lesser degree in other indications, a limited search in ClinTrials.gov revealed nearly 95 non-oncology industry sponsored adaptive trials over the past decade. 

    Regulatory Perspective on Adaptive Designs

    As interest in flexible design elements grows across all indications, both the FDA and EMA have issued updated guidance on adaptive trial designs for drugs and biologics in recent years [3, 4]. For early phase exploratory studies, the FDA touts the advantages of an adaptive design that advises dosing, pharmacokinetic (PK) and pharmacodynamic (PD) responses, which may improve the design and possibly the chances of success of later-phase trials [3]. 

    Adaptive Early Clinical Trial Designs

    For single ascending dose (SAD) and multiple ascending dose (MAD) studies, adaptive design elements can be incorporated into the study protocol to add flexibility. This can be a valuable approach when there are still many unknowns in the initial clinical drug development phases. Case examples of recent adaptive protocols are highlighted in Table 1. These elements, such as alterations to drug dose, number of cohorts, or schedules of PK sampling and PD assessments, must be pre-specified in the protocol. For each adaptable component, limits should be set to address any safety concerns and to operate within acceptable risk parameters [5]. For example, if a blood sample schedule can be adjusted to optimize evaluable PK or PD data, the maximum number of blood draws should be noted in the protocol and not exceeded. 

    Table 1. Case Studies of Early Clinical Trial Adaptive Study Designs

    Case Study Study Design Adaptive Elements Implementation
    Adaptive Dose and PK 2-part SAD and MAD study in healthy volunteers Drug dose, infusion volume and/or rate, PK schedule (time points and number of samples) Adaptive elements were modified based on AEs, clinical finding, safety and tolerability resultsProtocol allowed for reduced PK sample number if data permitted 
    Adaptive Cohort Number SAD study in healthy volunteers Cohort number and dose levels defined for groups 1-5 Option to add up to 2 additional cohorts  Upon review of cohort 1-5 safety and PK data, the decision will be taken to continue with increased dose levels, or an intermediate dose, or to cancel cohorts 6-7  
    Adaptive PD Response MAD study in participants with obesity Number of PD assessments  Multiple PD assessments evaluated in cohort 1 with option to omit or adjust PD schedule in subsequent cohorts Protocol also indicated the maximum number of PD assessments that can be taken
    Adaptive Sample Size Fixed-dose combination vs free dose cross-over bioequivalence (BE) study in healthy volunteers Sample size re-estimation Clinical study activity paused during COVID-19 pandemic before all participants completed cross-over scheme   Adaptive and interim analysis was performed to re-evaluate  study sample size and power, using a validated method for crossover BE design [6]. Trial results demonstrated BE based on completed participant data [7]

    Advantages of Adaptive Early Clinical Trials

    With pre-defined adaptive protocol elements, no amendments are required, which can save time and result in scheduling efficiencies. In the case of future pandemic outbreaks or other extraordinary situations, adaptive designs can serve as a mitigation step and potentially ‘save’ a study from timely delays or the need to repeat the trial. This approach was applied in a BE study, where sample size was re-assessed midway through trial conduct using validated statistical methods to complete the trial without further interruption from a COVID-19 outbreak [7]. Ultimately, the advantage of adaptive, early clinical trial designs can lead to both time and costs savings. Celerion’s Protocol Design and Development Scientists are trial experts and can design early clinical trials with flexible and adaptive elements to get the most out of a study, for less.

    References

    1. Pallmann P et al. BMC Med. 2018;16(1):29.   

    2. Bothwell LE et al. BMJ Open. 2018;8(2):e018320.

    3. Food and Drug Administration. Adaptive Designs for Clinical Trials of Drugs and Biologics  Guidance for Industry. 2019. https://www.fda.gov/media/78495/download.   

    4. European Medicines Agency. Adaptive Pathways. https://www.ema.europa.eu/en/human-regulatory/research-development/adaptive-pathways    

    5. Lorch U et al. BMC Med Res Methodol. 2014;14:84.   

    6. Potvin D et al. Pharm Stat. 2008;7(4):245-62.   

    7. Csonka D et al. Pharmacol Res Perspect. 2021;9(5):e00846.